
Medicare Advantage Plan or a Medicare Supplement Plan?
The decision between Medicare Advantage (Part C) and a Medicare Supplement (Medigap) policy dictates how you access doctors, manage healthcare costs, and protect your retirement savings. Get an expert, unbiased breakdown for 2026.
Schedule a Free Educational ReviewWhat Is the Main Difference Between Medicare Advantage and Medigap?
If you stripped away all the fine print, the single main difference comes down to who controls your healthcare and how you pay for it:
Medicare Supplement (Medigap)
“Pay Premium Upfront for Total Freedom”
- Who is in charge: The federal government (Original Medicare) manages your care. Private Medigap simply pays the leftover bills.
- How costs work: You pay a higher monthly premium upfront, but enjoy minimal out-of-pocket costs when receiving medical care.
- Doctor choice: You can visit any doctor or hospital in the entire U.S. that accepts Medicare—no networks, no referrals, no prior authorization required.
Medicare Advantage (Part C)
“Pay As You Go with Managed Local Networks”
- Who is in charge: A private insurance carrier (like Humana, Aetna, or UnitedHealthcare) replaces Original Medicare to manage your care.
- How costs work: You pay a $0 or very low monthly plan premium upfront, but pay copays or coinsurance as you get care, up to an annual maximum limit.
- Doctor choice: You must use local provider networks (HMO or PPO), get prior approvals for complex procedures, and may need specialist referrals.

The Fundamental Split: Pay-As-You-Go vs. Pay-Upfront Predictability
Original Medicare (Parts A and B) covers medically necessary hospital and outpatient care. However, it leaves significant financial gaps: a $1,736 hospital deductible per benefit period in 2026, a 20% uncapped coinsurance on doctor visits and outpatient therapies, and zero routine prescription drug benefits.
To shield yourself from unlimited medical liabilities, Medicare requires you to choose one of two distinct insurance pathways:
Pathway 1: Original Medicare + Medigap + Standalone Part D
How it works: The federal government remains your primary insurer. You buy a private Medicare Supplement (Medigap) plan to pay Original Medicare’s copays, deductibles, and coinsurance, and add a separate Part D prescription plan for medications.
Financial Philosophy: Pay a higher, predictable premium every month upfront so that when you visit doctors or hospitals, your out-of-pocket costs are zero or near-zero.
Pathway 2: Medicare Advantage (Part C)
How it works: You opt out of government-administered Original Medicare and join a Medicare-approved private insurance plan (HMO, PPO, or PFFS). The carrier receives a monthly subsidy from Medicare to manage your complete care.
Financial Philosophy: Pay a $0 or low monthly plan premium upfront, but pay copays and coinsurance as you receive medical services, up to an annual maximum limit.
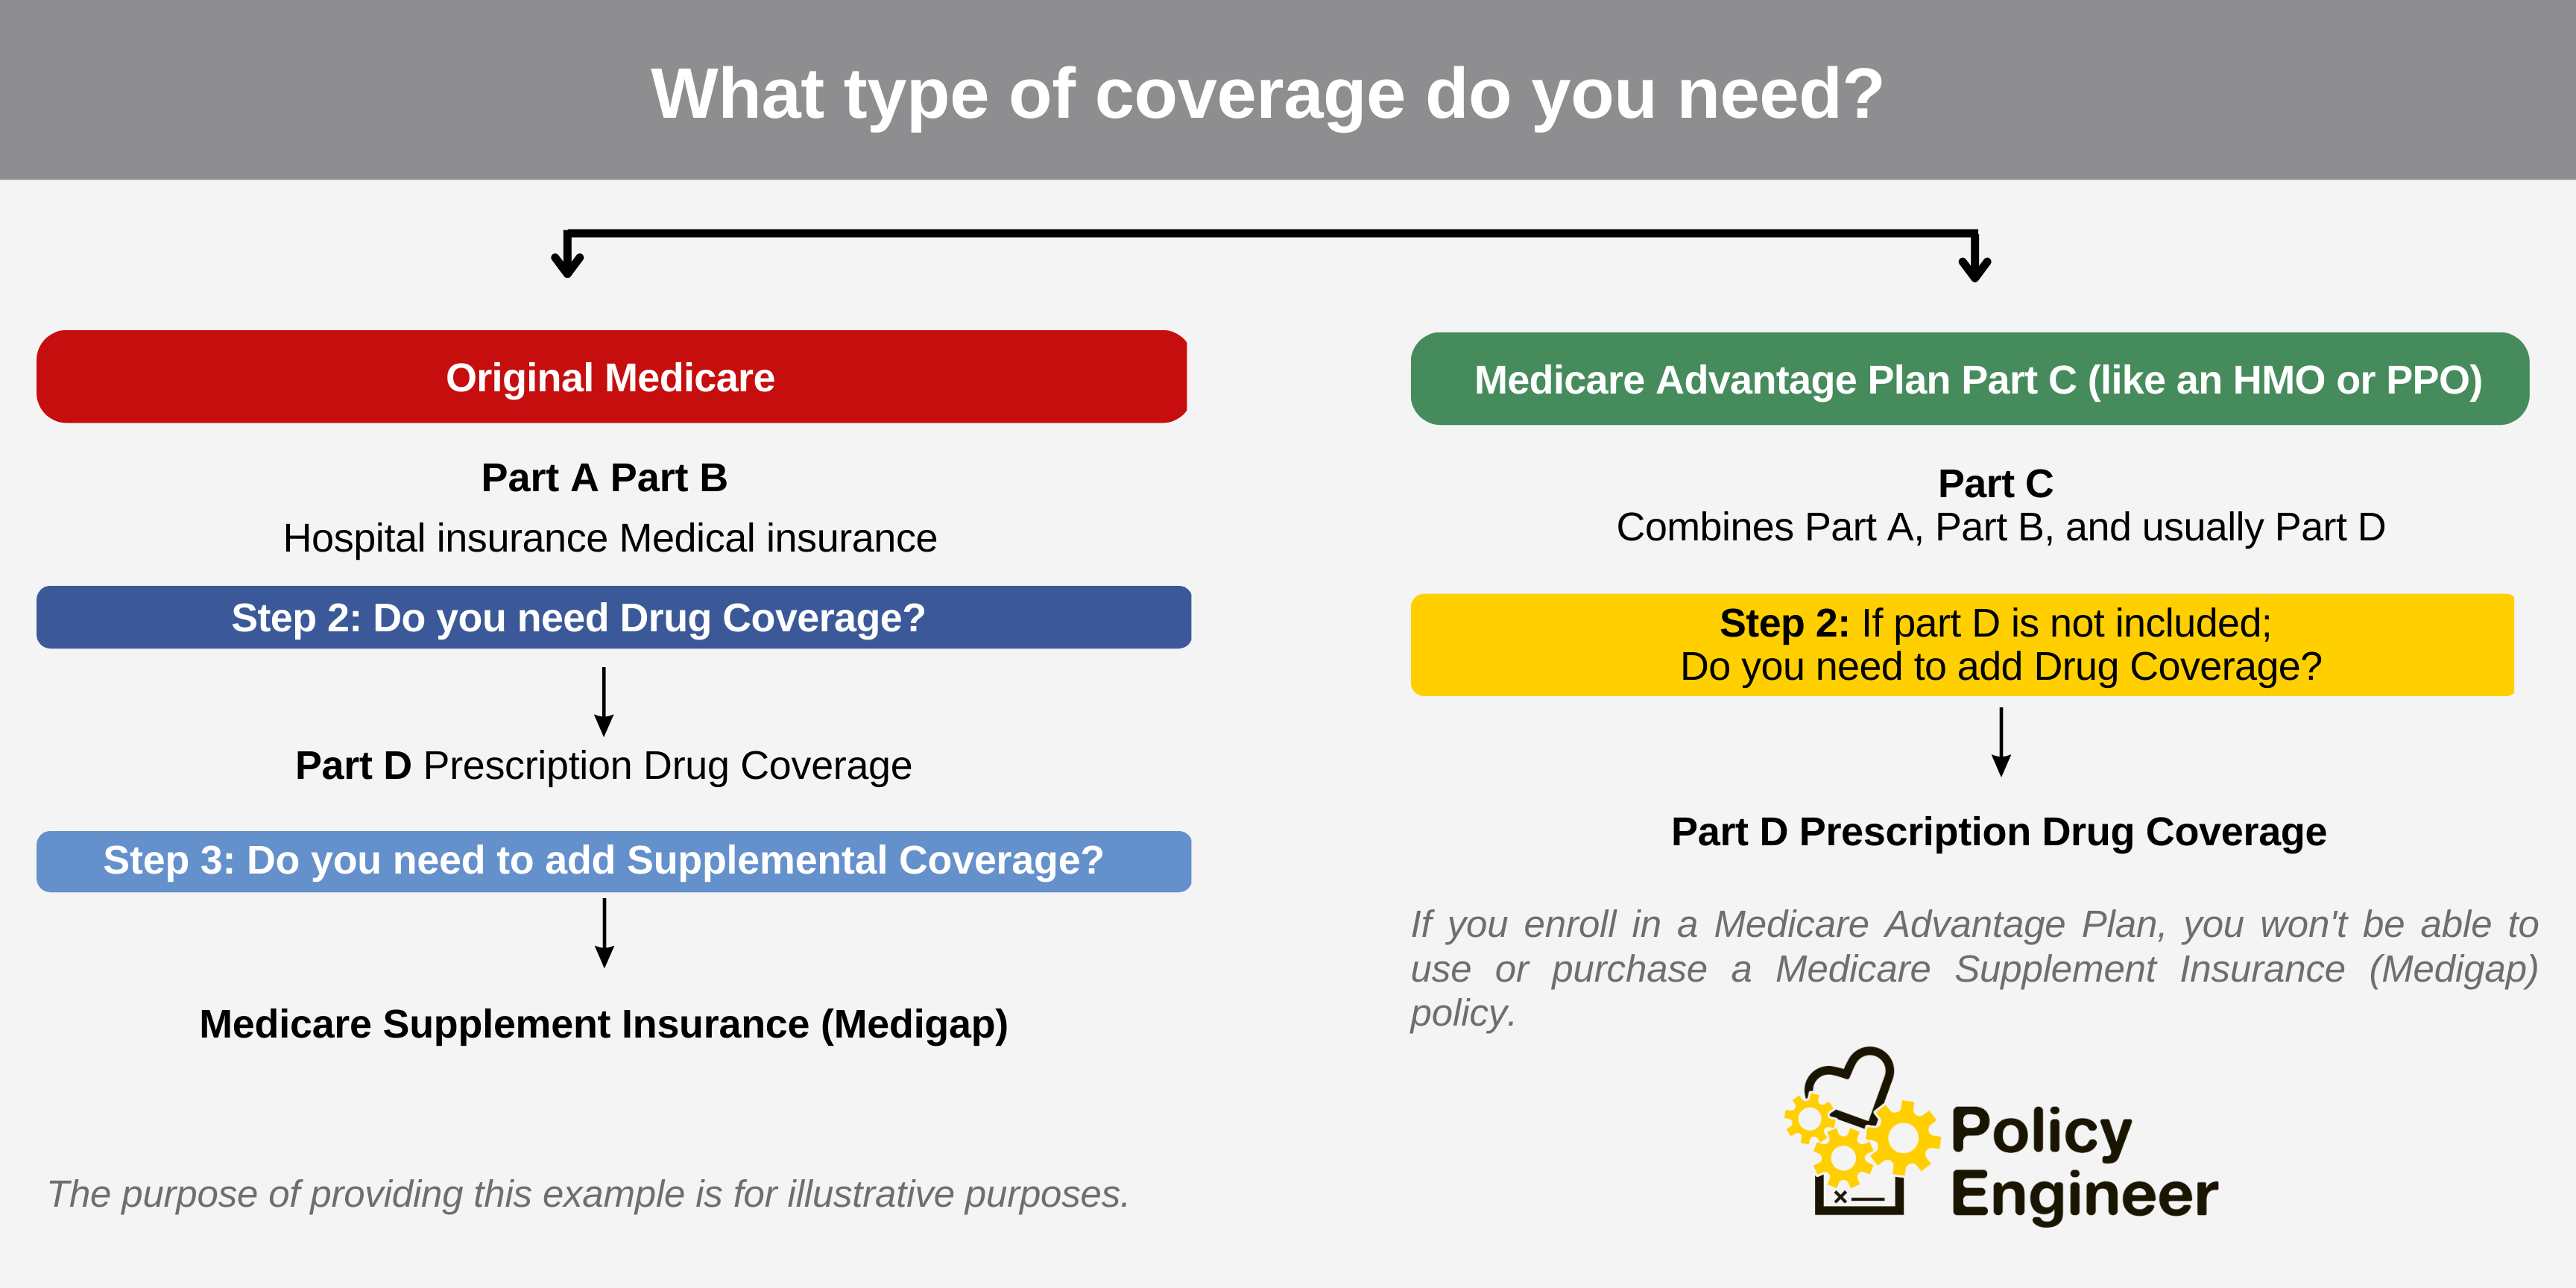
2026 Master Comparison: Medigap vs. Medicare Advantage
This side-by-side breakdown compares how both options function across real-world medical and financial categories:
| Category | Medicare Supplement (Medigap) | Medicare Advantage (Part C) |
|---|---|---|
| Primary Payer & Administration | Federal Medicare pays first; Medigap pays second. | Private Insurance Company (e.g., UnitedHealthcare, Humana, Aetna) replaces Original Medicare. |
| Monthly Plan Cost | Higher Premium: $100–$250+/month (plus standard Part B premium of $202.90 and separate Part D drug premium). | Low or $0 Premium: Many $0 monthly plans available (must still pay standard $202.90 Part B premium). |
| Out-of-Pocket Expenses at Care | Predictable/Near Zero: Plan G covers 100% of covered medical costs after meeting the annual Part B deductible ($283 in 2026). | Pay-As-You-Go: Fixed copays for doctor visits ($5–$50), specialist visits ($35–$90), hospital stays ($300–$450/day), and chemotherapy (20%). |
| Annual Out-of-Pocket Cap (MOOP) | Not required because coverage leaves virtually no out-of-pocket medical expenses behind. | Mandatory Cap: Federal maximum in 2026 allows caps up to $8,850+ for in-network care (higher for combined in/out-of-network PPOs). |
| Doctor & Hospital Networks | Nationwide Freedom: See any doctor, specialist, or health system in the U.S. that accepts Medicare. No local network restrictions. | Restricted Networks: HMOs require in-network care (except emergencies). PPOs allow out-of-network care at substantially higher copays. |
| Referrals & Prior Authorizations | No Referrals Needed: Direct access to specialists. Prior authorization is virtually non-existent for Medicare-covered services. | Prior Authorization Required: Insurer must pre-approve MRIs, CT scans, surgeries, chemotherapy, and skilled nursing stays before care is delivered. |
| Prescription Drug Coverage | Requires a separate standalone Part D Drug Plan (beneficiaries benefit from the 2026 $2,000 annual pharmacy spending cap). | Usually integrated directly into the plan (MAPD). Formulary and drug tiers are set by the individual plan carrier. |
| Routine Dental, Vision & Extras | Does not cover routine dental cleanings, eyeglasses, or gym memberships. Must purchase standalone policies if desired. | Frequently offers bundled allowances for routine dental, eye exams/glasses, hearing aids, OTC allowances, and gym memberships. |
| Yearly Policy Stability | Guaranteed Standardized Benefits: A Plan G sold today offers the exact same core benefits 10 years from now. Insurers cannot alter benefits annually. | Annual Contract Changes: Premiums, copays, provider networks, and drug formularies can change every January 1 via the Annual Notice of Change (ANOC). |
In-Depth: Understanding Medicare Advantage (Part C)
Medicare Advantage plans operate like employer health plans. The federal government pays private insurers a fixed capitated rate per month to manage your care. While these plans offer initial cost savings, understanding their mechanics is essential.
The Real Perks of Part C
- Immediate Monthly Savings: For healthy individuals on fixed incomes, paying $0 in plan premiums frees up monthly cash flow.
- Convenient All-In-One Bundling: One insurance card manages medical care, hospital admissions, prescription drug coverage, and wellness perks.
- Value-Added Benefits: Free SilverSneakers gym memberships, quarterly OTC allowance cards for pharmacy items, and routine dental cleanings.
The hidden friction points in Medicare Advantage
- Prior Authorization Delays: According to OIG reports, Medicare Advantage plans frequently require pre-approval for complex treatments, physical therapy, and inpatient rehabilitation, which can cause care delays.
- Annual Network Churn: Hospital systems, major medical centers, and private physicians can leave or be dropped from a plan’s network at the end of any calendar year.
- Regional Limitations: Coverage is generally limited to your local service area (county or multi-county region). Seeking non-emergency care while traveling or wintering out-of-state can lead to full out-of-pocket costs on HMO plans.
In-Depth: Understanding Medicare Supplement (Medigap)
Medigap plans do not replace Original Medicare—they work alongside it. Federal law standardizes Medigap policies by letter (Plans A, B, C, D, F, G, K, L, M, N). A Plan G from Carrier A provides the exact same medical benefits as a Plan G from Carrier B; only the monthly premium and customer service differ.
Medigap Plan G vs. Medigap Plan N (The Top 2 Choices in 2026)
Because Plans C and F are closed to enrollees who turned 65 after January 1, 2020, Plan G and Plan N represent the vast majority of new enrollments:
Medigap Plan G (Maximum Coverage)
What it covers: 100% of Original Medicare’s gaps after you pay the annual Part B deductible ($283 in 2026).
Out-of-pocket experience: Covers all inpatient hospital deductibles, 20% doctor coinsurance, excess charges, and skilled nursing coinsurance. Once your $283 deductible is met, you pay $0 for all Medicare-covered medical care for the rest of the year.
Best for: Individuals wanting maximum peace of mind and zero copays at medical visits.
Medigap Plan N (Cost-Sharing Value)
What it covers: Similar to Plan G, but with lower monthly premiums in exchange for small copays and no coverage for Part B excess charges.
Out-of-pocket experience: You pay the Part B deductible ($283 in 2026). Afterward, you pay a copay of up to $20 per doctor visit and up to $50 per emergency room visit (waived if admitted).
Best for: Healthier individuals who want Medigap network freedom at a lower monthly premium.
Underwriting, Guaranteed Issue & Trial Rights
One of the most dangerous misunderstandings in Medicare is assuming you can easily switch from Medicare Advantage to Medigap whenever you get sick. Understanding these enrollment rules prevents long-term insurance traps.
Timing your Medigap enrollment correctly is critical to avoiding medical underwriting:

1. The 6-Month Medigap Open Enrollment Window
Your one-time primary window starts the month you are age 65 or older AND enrolled in Medicare Part B. For 6 months, you have a federal **Guaranteed Issue Right** to purchase any Medigap plan sold in your state. Insurers cannot deny you coverage, charge higher premiums due to pre-existing health conditions, or impose waiting periods.
2. Medical Underwriting Outside Open Enrollment
If you apply for a Medigap plan outside your 6-month window or try to switch from Medicare Advantage back to Medigap years later, insurers in most states subject you to medical underwriting. They can review your medical history, prescriptions, and diagnoses—and can reject your application or charge significantly higher rates for conditions like diabetes, heart disease, rheumatoid arthritis, or past cancer history.
3. The 12-Month Medicare Advantage “Trial Right”
Federal law provides a safety net known as a **Trial Right** under two specific conditions:
- Trial Right #1 (Turning 65): If you join a Medicare Advantage plan when you first become eligible for Medicare at age 65, you have 12 calendar months to test the plan. If you disenroll within those first 12 months, you have a guaranteed right to switch back to Original Medicare and buy any Medigap plan without health questions.
- Trial Right #2 (Dropping Medigap): If you dropped a Medigap policy to join a Medicare Advantage plan for the very first time, and you’ve been in the Advantage plan for less than 12 months, you have the right to return to your previous Medigap policy.
Real-World Scenarios: Which Persona Fits You?
Profile: Splits time between cold winter states and warm southern states, or travels extensively across the U.S. in an RV.
Recommended Path: Medigap (Plan G or N) + Standalone Part D. Out-of-state Medicare Advantage networks create extreme friction for seasonal residents. Medigap allows you to see any specialist or visit any hospital nationwide that accepts Medicare.
Profile: Needs to minimize fixed monthly overhead expenses and values extra perks like routine dental care and gym access.
Recommended Path: Medicare Advantage (Part C). Utilizing a $0 monthly premium plan keeps upfront expenses low, while the plan’s Maximum Out-of-Pocket (MOOP) cap prevents catastrophic financial events.
Profile: Expects frequent physician visits, ongoing specialist care, physical therapy, or wants total freedom to choose top cancer research centers (e.g., Mayo Clinic, MD Anderson) without needing prior authorization.
Recommended Path: Medigap (Plan G) + Standalone Part D. Provides completely predictable medical billing and direct access to top medical institutions across the country.
Your 5-Point Selection Checklist
Before committing to a Medicare plan pathway, evaluate these five crucial criteria:
1. Physician & Hospital Access
Are your primary doctors, preferred specialists, and preferred regional hospital systems in-network for the Medicare Advantage plans you are evaluating? With Medigap, as long as the provider accepts Medicare, network restrictions do not apply.
2. Total Annual Cost Projections
Calculate your total annual financial risk: (Monthly Premium × 12) + Expected Copays + Maximum Out-of-Pocket Exposure. Compare this against Medigap’s predictable annual total cost.
3. Prescription Drug Needs
List all daily prescription drugs, dosages, and preferred pharmacies. Check these against both Medicare Advantage formularies and standalone Part D plans to confirm medication coverage under the 2026 $2,000 out-of-pocket drug cap.
4. Travel & Geographic Lifestyle
Do you live in more than one state during the year, or do you travel outside your home county frequently? If yes, Medigap avoids out-of-network coverage penalties.
5. Long-Term Health Flexibility
Consider your long-term health trajectory. Enrolling in Medigap when turning 65 guarantees access without medical underwriting. Switching to Medigap years later may not be possible if health conditions develop.
Frequently Asked Questions (FAQ)
1. Is Medicare Advantage better than Medigap?
Neither pathway is universally superior. Medicare Advantage offers low or $0 monthly plan premiums and bundled dental/vision perks, but requires network compliance and copays. Medigap offers nationwide provider freedom and near-zero out-of-pocket care costs, but requires higher monthly premiums. The best choice depends on your financial priorities and medical needs.
2. Can I drop my Medicare Advantage plan and get a Medigap plan at any time?
No. You can only disenroll from a Medicare Advantage plan during standard enrollment windows (such as the Fall Annual Enrollment Period from Oct 15 – Dec 7 or the Medicare Advantage Open Enrollment Period from Jan 1 – Mar 31). Additionally, enrolling in a Medigap plan outside your initial 6-month window generally requires passing medical health questions, unless you qualify for a specific Guaranteed Issue Right or 12-month Trial Right.
3. Do Medigap plans cover prescription drugs?
No. Standardized Medigap policies sold after January 1, 2006, do not include prescription drug coverage. Beneficiaries with Medigap policies purchase a standalone Medicare Part D plan to cover pharmacy medications. In 2026, Part D prescription plans feature a strict $2,000 annual out-of-pocket limit on covered drugs.
4. What happens if my doctor stops taking my Medicare Advantage plan mid-year?
Insurance networks can change throughout the year. If your provider drops out of network, you generally must select another in-network provider or pay higher out-of-network rates until the next open enrollment period allows you to switch plans.
5. Why do Medigap premiums vary between insurance carriers for the exact same plan letter?
Because Medigap plans are standardized by the federal government, a Plan G with Company A offers identical coverage to a Plan G with Company B. However, private insurance carriers set their own rates based on rating structures (Community-rated, Issue-age-rated, or Attained-age-rated), administrative overhead, and underwriting pool performance in your specific zip code.
6. Do both options require me to keep paying my Medicare Part B premium?
Yes. Regardless of whether you select Medicare Advantage or Medigap, you must continue paying your standard monthly Medicare Part B premium ($202.90 baseline in 2026, or higher if subject to income-based IRMAA surcharges).
Need Assistance Choosing Between Medigap & Advantage?
Schedule a free, educational review with our Medicare experts to analyze local plan networks, check prescription drug costs, and receive custom Medigap rate quotes.
Schedule Educational Review
Not affiliated with or endorsed by the government or the federal Medicare program.
Medicare.gov is the official U.S. government website for Medicare information.